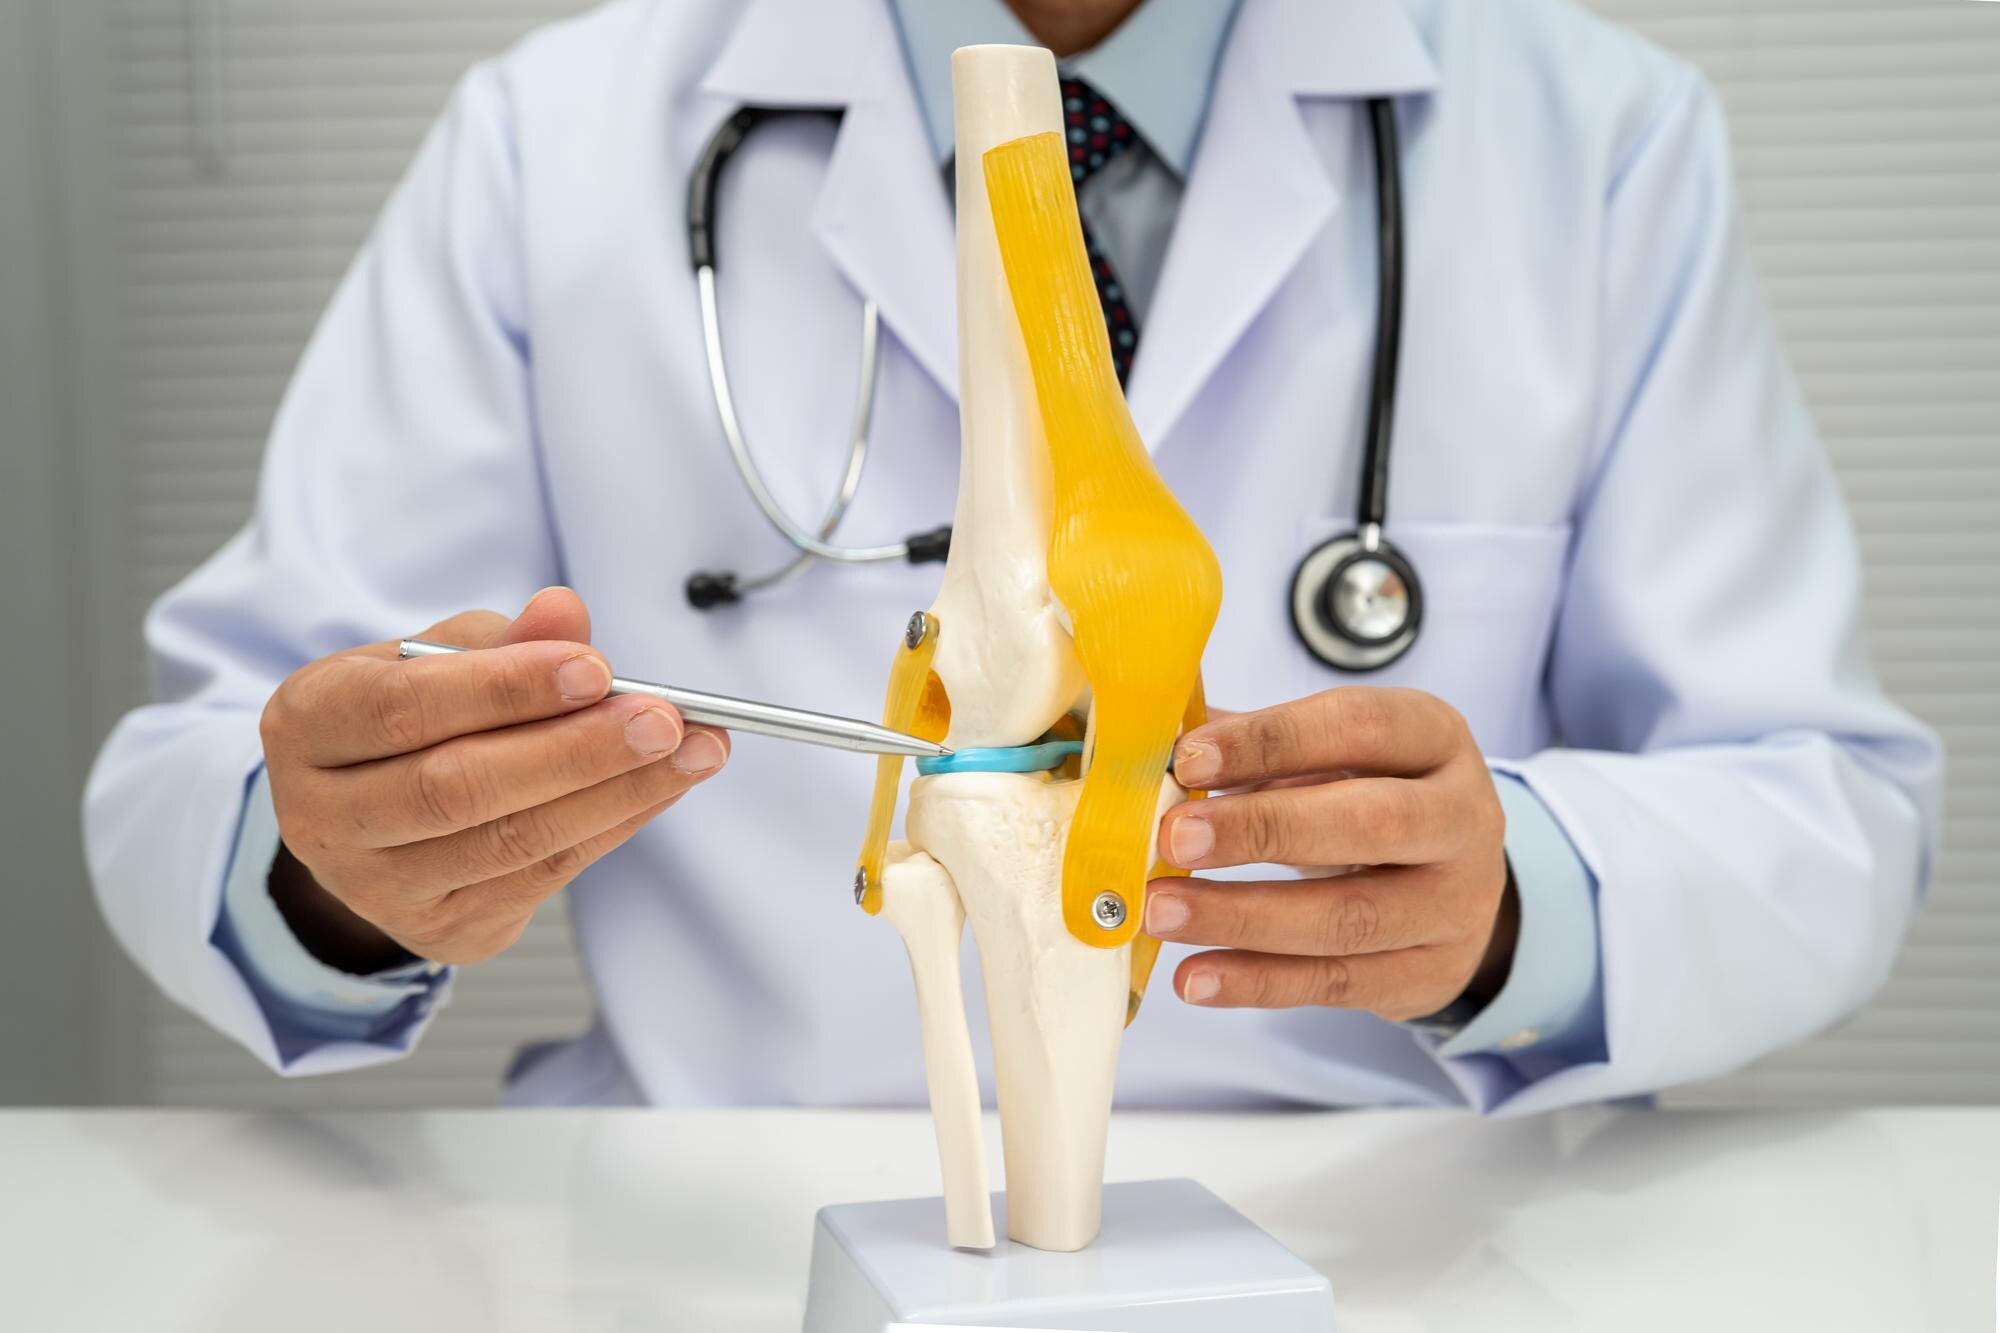
Stiffness after sitting, difficulty using stairs or gripping objects, and pain that eases after gentle movement can signal an early joint problem. Knowing which symptoms need assessment, what treatment involves and how to progress exercise safely can help you protect mobility before weakness and movement avoidance become established.
Key takeaways
- Activity-related pain and stiffness after rest point toward early osteoarthritis.
- A clinician uses your symptoms, examination and selective imaging to confirm the cause.
- Exercise, weight management and pain relief usually come before surgery.
- Review care when pain, swelling or mobility problems persist or worsen.
Which early symptoms suggest osteoarthritis rather than ordinary stiffness?
Early osteoarthritis symptoms usually combine activity-related joint pain with joint stiffness after rest that lasts about 30 minutes or less. The discomfort often eases after gentle movement but returns with walking, stairs, standing or repeated hand use.
| Feature | Ordinary stiffness | Possible early osteoarthritis |
|---|---|---|
| Pain pattern | Settles as you move and does not repeatedly follow the same activity | Returns with weight-bearing or repeated use |
| Stiffness after rest | Brief and occasional | Recurrent after sitting, waking or inactivity |
| Movement | Normal range once loosened | Reduced range of motion, such as difficulty fully bending a knee |
| Daily tasks | Little effect | Difficulty climbing stairs or gripping jars, tools or door handles |
Book a medical assessment when these symptoms persist for several weeks, interfere with work or sleep, or make you avoid normal activity. Early assessment can address pain, weakness and movement avoidance before they become established problems.
Do not assume every stiff joint is osteoarthritis. A hot, markedly swollen joint, fever, sudden severe pain, an injury, or morning stiffness lasting longer than 30 minutes needs prompt assessment for causes such as gout, infection or inflammatory arthritis. Seek urgent care for a red, hot joint with fever or an inability to bear weight.
A clinician can then examine the joint and distinguish osteoarthritis from tendon, bursa, meniscus or spine-related problems.
How does a clinician confirm osteoarthritis and rule out other causes?
An osteoarthritis diagnosis is usually clinical: the clinician matches your symptom pattern with examination findings rather than relying on a scan. Activity-related pain, reduced movement and morning stiffness lasting about 30 minutes or less support osteoarthritis.
During the initial assessment, expect:
- Questions about the affected joint, pain triggers, stiffness after rest, previous injury and changes in walking, stairs, gripping or daily tasks.
- A joint examination checking tenderness, swelling, warmth, crepitus, stability and range of motion.
- A gait assessment to identify limping, altered alignment or movement that shifts stress onto another joint.
- Strength testing for osteoarthritis, which identifies muscle weakness that could be worsening instability or mobility.
X-rays are not routinely needed when the pattern is typical. A weight-bearing X-ray becomes useful when symptoms are unusual, the diagnosis is uncertain, pain is severe or persistent, or a fracture, deformity or advanced joint-space narrowing needs checking. X-ray changes do not always match pain severity.
A hot, markedly swollen joint, fever or morning stiffness lasting well beyond 30 minutes points away from straightforward osteoarthritis. Further assessment may include:
- Blood tests such as C-reactive protein, erythrocyte sedimentation rate, rheumatoid factor or anti-CCP antibodies for suspected inflammatory arthritis.
- Uric acid testing or joint-fluid aspiration when gout is possible.
- Ultrasound or MRI for tendon injury, bursitis, meniscal damage or pain referred from the spine.
What does early osteoarthritis treatment involve before surgery?
A useful early osteoarthritis treatment plan combines symptom control with actions that keep you moving. The aim is not to restore worn cartilage, but to reduce pain, build strength and preserve daily function before stiffness and movement avoidance become established.
| Treatment | Main purpose | Practical point |
|---|---|---|
| Exercise and physiotherapy | Improve strength, joint movement and confidence | Use a graded programme rather than resting through pain |
| Activity modification | Reduce aggravating loads without stopping movement | Change stair use, lifting, kneeling or work positions; avoid prolonged inactivity |
| Weight management for osteoarthritis | Reduce load on weight-bearing joints | Any loss can help; losing 10% of body weight usually helps more than 5% |
| Topical NSAID knee osteoarthritis treatment | Reduce local pain and inflammation | Apply as directed; check the label for skin precautions and maximum use |
| Oral NSAID | Provide stronger short-term pain relief | Review stomach, kidney, liver and cardiovascular risks, medicine interactions and gastroprotection |
These treatments work together: medication can make walking or exercise manageable, while strengthening and activity changes support function after the medicine is stopped. A clinician or pharmacist should check oral NSAIDs before you use them, especially if you have ulcers, kidney disease, heart disease or take blood thinners.
Do not assume that an arthritic knee needs “cleaning out.” Arthroscopic lavage or debridement does not treat osteoarthritis alone; locking or another mechanical problem needs separate assessment. Surgery becomes a discussion when pain and mobility limits remain substantial despite a properly followed non-surgical programme.
Which exercises improve mobility without provoking a flare?
Choose a level of movement that leaves the joint looser, not more painful. Osteoarthritis exercises work best as regular, manageable doses: mild discomfort during activity is acceptable when it settles within a few hours and is no worse the next morning.
| Option | How to use it | Stop or adjust when |
|---|---|---|
| Range-of-motion exercises | Slowly bend and straighten the joint, or perform heel slides, within a comfortable range. Use 5 to 10 repetitions, several times daily. | Do not force a sharp catch, strong pain, or a blocked movement. |
| Quadriceps strengthening | Tighten the front thigh while the leg is straight, or use a supported sit-to-stand. Hold for 5 seconds and repeat 5 to 10 times. | Reduce the range or repetitions if pain increases during stairs, standing, or later that day. |
| Low-impact aerobic exercise | Walk on level ground, cycle, or exercise in water for short intervals. Build towards regular sessions by adding a few minutes at a time. | Replace walking with cycling or water exercise when impact causes limping or lingering pain. |
If movement is painful, warm up with gentle range-of-motion exercises before strengthening or aerobic activity. During a flare, cut the duration and resistance rather than stopping all movement; resume progression once symptoms return to your usual level.
A swollen, hot joint, fever, or pain that remains significantly worse the next day needs clinical review. A physiotherapist can adapt quadriceps strengthening when weakness, poor balance, or fear of movement limits safe practice.
How much ongoing effort does early treatment require, and when should care be reviewed?
Ongoing treatment is usually a maintenance routine, not a short course that ends when pain improves. Keep exercising within tolerable limits, adjust demanding tasks and review progress when stiffness, walking distance or everyday function stops improving.
Use this checklist:
- Follow your osteoarthritis physiotherapy plan consistently, including mobility and strength work. Reduce intensity during a flare rather than stopping all movement.
- Apply pacing and ergonomic changes: alternate activity with rest, avoid long static positions, use a higher chair if rising is difficult, and change repetitive work methods.
- Consider walking aids and braces when pain is substantial, another joint is affected, instability is present, or exercise alone has not corrected abnormal loading. Have the aid fitted and learn to use it safely.
- Arrange a review if pain, stiffness, limping, instability or loss of function continues after the agreed non-surgical treatment period. Bring a note of walking tolerance, painful tasks, exercise response and medication problems.
- Ask Dr DineshRam Orthopedician ECR to reassess the diagnosis if symptoms change, function declines or treatment produces no meaningful gain.
Persistent pain, stiffness, reduced function or progressive deformity that limits work, sleep, self-care or participation supports a joint replacement referral after appropriate non-surgical care. Referral should reflect your quality of life, not an X-ray grade alone, and age, smoking, comorbidity or body-mass index should not be used as automatic exclusions.
Routine arthroscopic “cleaning out” is not a substitute for this pathway.
Related services
OSTEOARTHRITIS often referred to as “wear-and-tear arthritis,” is a condition that affects your joints. |
Joint injections are an effective, minimally invasive treatment for pain and inflammation in joints caused by conditions like arthritis, bursitis, or... View service → |
Frequently asked questions
Which early symptoms suggest osteoarthritis rather than ordinary stiffness?
Activity-related joint pain and stiffness after rest lasting about 30 minutes or less suggest osteoarthritis. Symptoms often ease with gentle movement and return with walking, stairs, standing or repeated hand use.
How does a clinician confirm osteoarthritis and rule out other causes?
A clinician reviews your symptom pattern, examines the joint and orders imaging when needed. They assess for signs of injury, inflammatory arthritis, gout, infection or another condition that needs different treatment.
What does early osteoarthritis treatment involve before surgery?
Treatment may include a tailored exercise programme, activity changes, weight management when relevant, physiotherapy and pain-relief options. Surgery is considered when symptoms remain disabling despite appropriate non-surgical care.
Which exercises improve mobility without provoking a flare?
Start with gentle range-of-motion exercises, low-impact walking, cycling or water exercise, then add strengthening gradually. Reduce intensity if pain sharply increases, swelling develops or symptoms remain worse the next day.
How much ongoing effort does early treatment require, and when should care be reviewed?
Early treatment works through regular movement, strengthening and practical activity changes rather than a single appointment. Arrange a review when pain or stiffness worsens, mobility declines, swelling persists or your exercise plan triggers repeated flares.
Related services
Pain can significantly impact your daily life, making even the simplest tasks difficult. Whether it’s acute or chronic, pain should never be ignored. View service → |
Physiotherapy plays a crucial role in restoring movement, relieving pain, and preventing further injury. View service → |
Spine conditions can have a big impact on your daily life, affecting your ability to move, maintain good posture, and even perform simple tasks. View service → |